Melanoma without the typical dark colour
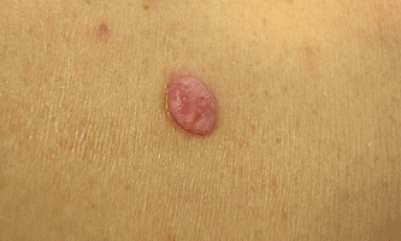
Amelanotic melanoma has little or no visible pigment. It may therefore be pink, red, purple, whitish or similar to the surrounding skin. “Amelanotic” describes a feature of the lesion, not a stage or necessarily a separate subtype: several common types of melanoma can have this presentation.
Hypomelanotic melanoma retains reduced or partial pigmentation. In practice these terms can describe closely related appearances, but diagnosis rests on the combined clinical and histological findings. A pale colour does not mean the cells are not melanocytic and does not automatically make the tumour less dangerous.
Difficulty recognising these lesions may contribute to delayed diagnosis. It is not correct, however, to attribute increased incidence to that difficulty: disease frequency and diagnostic delay are different phenomena. Frequency estimates also depend on how reduced pigmentation is defined and recorded.
Appearance and changes to report
It may appear as a flat patch, papule or nodule at different skin sites, including the nail unit. Some lesions have small brown or black areas; others show no obvious pigment. Growth, changing shape or borders, ulceration and bleeding should be reported to a clinician.
Its appearance may resemble a pyogenic granuloma, basal or squamous cell carcinoma, a vascular lesion or inflammation. Resemblance to a common condition is not sufficient to identify it. A new growth that continues enlarging or a persistent lesion that does not heal deserves assessment.
The ABCDE rule remains useful but may be less intuitive without varied dark colours. Raised lesions also require attention to elevation, firmness and growth, summarised by EFG. Do not wait for pain, a large size or every warning sign to occur together.
Dermoscopy and histological confirmation
Dermoscopy may reveal residual pigment and abnormal vascular structures. Specialist descriptions include irregular, serpentine, hairpin, glomerular or corkscrew vessels, sometimes occurring together. These terms describe instrument-based observations: none proves melanoma on its own, and similar patterns can occur in other lesions.
When findings are suspicious, appropriate tissue sampling and histological examination are needed. The pathologist may use immunohistochemical stains to establish cellular origin and distinguish other tumours. Absence of visible pigment does not prevent melanoma from being identified in tissue.
The report should establish invasion, Breslow thickness, ulceration and margins alongside the diagnosis. Further investigations depend on these findings and clinical assessment, not on the lesion’s colour. A photograph can document change but cannot replace sampling when indicated.
Treatment and surveillance
Treatment follows melanoma principles and is selected mainly according to stage. Surgery is the main treatment for localised disease. When indicated, sentinel lymph node biopsy and additional investigations help complete staging. The word “amelanotic” alone does not require a different treatment.
Immunotherapy and targeted treatments may be used in appropriate settings, with targeted treatment requiring actionable molecular alterations. Radiotherapy and chemotherapy have selected uses; chemotherapy is not the usual first choice for advanced disease when suitable modern options are available. Age, general health, other illnesses and patient preferences contribute to decisions.
Follow-up includes the treated site, relevant lymph nodes and the rest of the skin. During skin self-examination, also look at pink or red lesions and areas without dark pigment. Prognosis depends mainly on disease extent and tumour features, so colour cannot provide an individual prediction.
Sources and update
- National Cancer Institute — Melanoma Treatment (PDQ)
- ESMO — Cutaneous melanoma: Clinical Practice Guideline (2025)
- DermNet — Amelanotic melanoma
Editorial revision: 16 October 2026. This information does not replace medical assessment.