Regional and distant metastases
Metastatic melanoma means melanoma cells have reached sites beyond their origin. It is not a primary subtype alongside nodular or superficial spreading melanoma: different common types of melanoma can spread. The key distinction is where the disease is located and whether it can be completely removed.
Regional lymph node involvement and certain regional skin or subcutaneous metastases may be stage III when distant metastases are absent. Spread to distant organs or sites defines stage IV. Regional and distant disease can coexist, so staging considers the complete picture.
Cells can spread through lymphatic channels or the bloodstream. An enlarged lymph node alone does not prove metastasis; infection and other explanations are possible. A new skin growth also needs assessment rather than automatic attribution to a previous tumour.
Local recurrence, satellites and in-transit metastases
Local recurrence is the return of disease at the treated site or near the scar. It is not synonymous with every lesion within a preset distance: local regrowth and metastatic deposits must be distinguished in their clinical and pathological context.
Satellite metastases are clinically visible skin or subcutaneous deposits within 2 centimetres of the primary melanoma. In-transit metastases lie farther away along the drainage territory before the regional lymph nodes. Microsatellites are identified under the microscope. These definitions contribute to staging and do not necessarily mean disease confined to a limb.
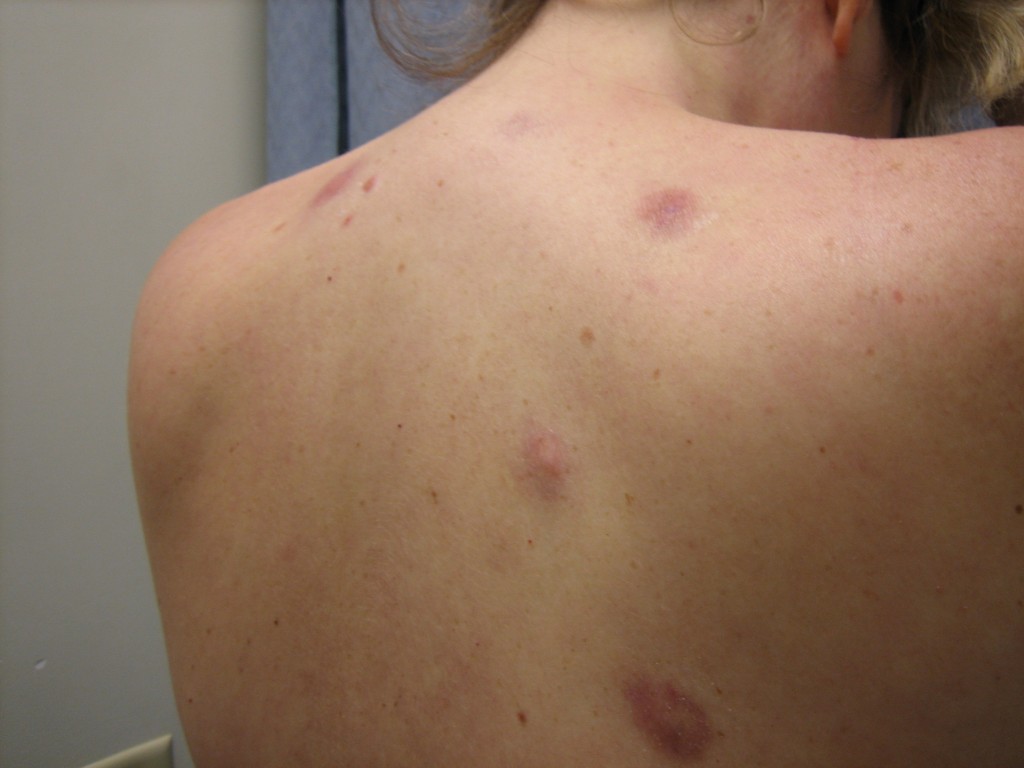
Lesions may appear as superficial or deep papules, plaques or nodules, pigmented or skin-coloured, and may be single or multiple. Shape and colour cannot establish their nature, extent or operability; biopsy confirmation is obtained when needed.
Which sites can be involved
Melanoma can involve lymph nodes, skin and subcutaneous tissues, including deposits in fat or muscle. Important visceral sites include the lungs, liver and brain; bones and the gastrointestinal tract may also be involved.
Other possible locations include the mediastinum, adrenal glands, kidneys, pancreas, spleen, thyroid, gallbladder and heart. This list describes possibilities rather than an individual ranking or a programme of indiscriminate testing. Frequencies vary with population, stage and detection methods; a historical table without that context cannot provide a reliable estimate for an individual.
Some metastases are detected before causing symptoms. Others produce site-related symptoms such as persistent cough, bone pain or neurological problems. Report new symptoms to the team; seizures, sudden neurological deficits or an unusually severe acute headache require urgent care.
Confirming and measuring disease
Assessment combines examination, clinical history, histological confirmation when obtainable and appropriate imaging. Lymph node ultrasound, CT, PET/CT and MRI, particularly brain MRI when indicated, answer different questions. X-rays and bone scans may have selected uses but are not a mandatory checklist for everyone.
Lactate dehydrogenase, or LDH, can contribute to prognostic assessment in advanced disease. It cannot diagnose or exclude metastases on its own: other conditions can raise it, and it can remain normal despite disease. Trends must also be interpreted alongside other findings.
Sentinel lymph node biopsy stages selected melanomas without clinically evident lymph node involvement. It is not the test used to confirm already known metastatic disease. A suspicious site instead requires sampling or further investigations appropriate to that situation.
In advanced disease, testing for BRAF mutations, particularly V600, may guide access to targeted treatment. Other molecular analyses are considered according to context. Results are discussed alongside affected sites, progression speed, symptoms and general health.
Current systemic treatments
Treatment has changed substantially since chemotherapy was the main option. Immune checkpoint inhibitors can reactivate the immune response against the tumour. Anti-PD-1 medicines such as pembrolizumab and nivolumab may be used alone or, in appropriate settings, in immunotherapy combinations. Combinations are not suitable for everyone and can increase toxicity.
When an actionable BRAF V600 mutation is present, combined BRAF and MEK inhibition may be considered. A diagnosis of melanoma alone does not make these medicines suitable. Selection and sequencing relative to immunotherapy depend on the clinical situation, contraindications and the need for disease control.
Authorised indications and reimbursement in Italy must be checked by the treating team. A medicine mentioned in an international source is not automatically available to every patient. Clinical trials may offer further possibilities for people meeting their eligibility criteria.
Dacarbazine and temozolomide are historical chemotherapy options. Chemotherapy may still have a role in selected cases but should not be presented as the usual first choice when appropriate modern options exist. Combining several chemotherapy drugs has not automatically been shown to improve survival and can increase adverse effects.
Report new symptoms promptly during treatment. Immune-related toxicities can affect different organs and require specific management. Patients receive personalised instructions and should not change treatment independently.
Surgery, radiotherapy and locoregional treatment
Metastatic disease does not always rule out surgery. Regional deposits or limited distant metastases may be treated locally in selected patients within an overall plan. Systemic treatment before or after surgery may also be discussed according to indication. Lymph node dissection is not automatic in every situation.
Radiotherapy can help control specific sites, including brain metastases or painful lesions. Technique, dose and combination with other treatments depend on lesion number, size and location and the person’s circumstances.
For in-transit metastases concentrated in a limb, specialist centres may consider isolated limb perfusion or infusion. Perfusion uses a circuit that limits systemic exposure and may deliver melphalan with hyperthermia and other agents according to protocol. There is no universal temperature for independent application, and interferon gamma should not be described as a standard component. These procedures primarily aim for regional control and do not guarantee a survival benefit.
Other local treatments, including electrochemotherapy or intralesional approaches, have selected indications. Topical agents such as imiquimod and contact sensitisers have been used in particular circumstances but are not standard systemic treatment for metastases. They require specialist decisions and cannot replace assessment of the whole disease.
Prognosis: interpreting updated figures
Older estimates of survival measured in a few months do not adequately describe everyone treated today. Some people achieve durable responses with modern therapies; others have resistant disease or conditions limiting their options. Disease sites and burden, LDH, general health, biological features and treatment response contribute to prognosis.
The US SEER programme reports five-year relative survival of 34.0% for cutaneous melanoma with distant spread at diagnosis, using SEER 21 excluding Illinois data for 2016–2022, both sexes and all racial categories. This is a US population statistic, not an Italy-specific estimate or a prediction for someone developing distant recurrence after an initially localised diagnosis.
Relative survival compares observed survival with expected survival in a similar population without that cancer. The figure combines people with different circumstances and treatments and reflects its observation period. It does not give a patient a five-year deadline or allow an individual response probability to be calculated independently.
Support and questions for the consultation
Supportive and palliative care can accompany anticancer treatment from the outset when helpful. It includes pain and symptom management and nutritional, psychological and social support. It does not mean abandoning active treatment and should not be reserved for the last days of life.
Ask which sites are involved, the stage, whether the disease is operable and whether molecular results are available. Clarify the treatment goal, alternatives, reassessment schedule, adverse effects to report and the contact to use urgently.
Keeping reports and a medicine list helps coordination between specialists and primary care. The pathway should be reassessed over time according to response and the person’s priorities. General information on this page cannot replace that discussion.
Sources and update
- National Cancer Institute — Melanoma Treatment (PDQ)
- ESMO — Cutaneous melanoma: Clinical Practice Guideline (2025)
- SEER — Melanoma of the Skin: Cancer Stat Facts
Editorial revision: 16 October 2026. This information does not replace medical assessment.