What desmoplastic melanoma is
Desmoplastic melanoma is a rare invasive melanoma variant featuring often spindle-shaped cells within collagen-rich tissue. Desmoplasia refers to this fibrous component. Conley and colleagues published its historical description in 1971, but diagnosis now relies on more detailed histological and immunohistochemical criteria.
It is seen mainly in older people, often in their sixth to eighth decades, and on chronically sun-damaged skin. The head and neck are important sites; the trunk, upper back and other areas can also be affected. Acral and mucosal locations have been described but are much less common. These patterns guide suspicion rather than providing exclusion criteria.
Fair skin and a history of sun exposure provide context but are not mandatory requirements. Restricting it to skin phototype I is incorrect. As with other common types of melanoma, the variant’s name cannot replace staging.
A scar-like lesion
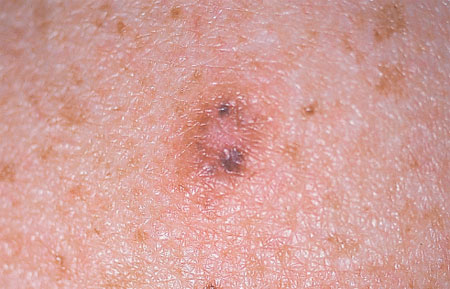
It may appear as a firm plaque or nodule that is skin-coloured, pink or poorly pigmented, sometimes with irregular pigmentation. Firmness and fibrosis may make it resemble a scar. An apparently scar-like lesion without an explanatory injury or procedure, or an area that progressively changes, needs assessment.
Clinical lookalikes include hypertrophic scars, dermatofibromas, neurofibromas and basal cell carcinomas. Dermoscopy may show pale areas, atypical vascular structures or pigmented components, but the appearance can remain nonspecific. Not every desmoplastic melanoma has the classic features of an asymmetrical dark patch.
Photographs help document location and evolution rather than resolve the diagnosis. Persistent growth, new firmness or altered sensation around the lesion should be reported to a clinician.
What the pathologist looks for
Histological examination requires representative tissue. Tumour cells may be slender and spindle-shaped, isolated or arranged in small bundles between collagen fibres within the papillary and reticular dermis, sometimes extending deeper. Atypia and mitotic activity vary: few visible mitoses do not exclude malignancy.
Lymphoid aggregates and macrophages may be present. Lymphoid aggregates can be a clue but are neither constant nor diagnostic by themselves. A superficial component may be associated with melanoma in situ, whereas an epidermal connection is not evident in other samples. A small biopsy may not represent the lesion’s full heterogeneity.
Microscopic differential diagnosis includes nerve-related lesions, moles and other spindle-cell or scar-like tumours. The pathologist therefore integrates morphology, location, clinical information and immunohistochemistry, with specialist review when necessary.
S100 and SOX10 are frequently expressed, whereas melanocytic markers such as Melan-A and HMB45 may be negative. Negative staining for the latter does not exclude desmoplastic melanoma. Other markers reported in specialist or historical panels, including tyrosinase, gp100/NKI-beteb, CD57 and CD68, should not be treated as a fixed signature; some can also highlight non-tumour cells. A single antibody result cannot establish a diagnosis independently.
Pure and mixed forms and neurotropism
Pure desmoplastic melanoma has a desmoplastic component comprising at least 90% of the invasive tumour. Mixed desmoplastic melanoma contains a significant non-desmoplastic invasive component. Classification requires adequate tissue and may be refined after complete excision.
This distinction has clinical implications: the pure form tends to have a lower risk of lymph node involvement than the mixed form. That does not mean it is always indolent or cannot spread. Thickness, ulceration, margins and stage remain essential.
Neurotropism means tumour growth along or around nerve structures. It can complicate local control and contribute to recurrence risk. When present, it should be recorded in the pathology report; pain alone, or the absence of symptoms, cannot establish whether it exists.
Treatment and multidisciplinary decisions
Surgery with appropriate margins is central to localised disease. Planning considers thickness, location, reconstruction, nerve involvement and any previously involved margins. In the head and neck, functional preservation needs particular attention while maintaining the goal of cancer control.
Sentinel lymph node biopsy is discussed according to individual risk, including the distinction between pure and mixed forms. Automatically excluding every desmoplastic melanoma from consideration is inappropriate. Decisions should be explained using the complete pathology findings.
Radiotherapy may be considered in selected situations to improve local control, for example when neurotropism and difficult margins create a high recurrence risk and further surgery is unsuitable. It is not mandatory in every case. Higher-risk or advanced disease may be considered for current systemic options, including immunotherapy, according to indications and patient circumstances.
Chemotherapy is not automatically the reference treatment. Targeted treatments require actionable molecular alterations. A multidisciplinary team can bring together surgery, oncology, radiotherapy and pathology.
Prognosis and follow-up
Prognosis should not be summarised as universally better or worse than every other melanoma. Local recurrence risk and lymph node spread are different issues, and their combination depends on the individual tumour. Subgroup statistics cannot replace individual assessment.
Follow-up examines the scar, nearby skin, relevant lymph nodes and the rest of the skin. Report new nodules or firmness, scar changes and persistent sensory symptoms. Investigation schedules are personalised; not everyone needs the same imaging tests.
Skin self-examination and sun protection support care without replacing clinical visits. Keep the pathology report and ask about pure or mixed classification, thickness, margins, neurotropism and the surveillance plan.
Sources and update
- National Cancer Institute — Melanoma Treatment (PDQ)
- ESMO — Cutaneous melanoma: Clinical Practice Guideline (2025)
- DermNet — Desmoplastic melanoma
- Desmoplastic melanoma — differential diagnosis
Editorial revision: 16 October 2026. This information does not replace medical assessment.