What primary mucosal melanoma means
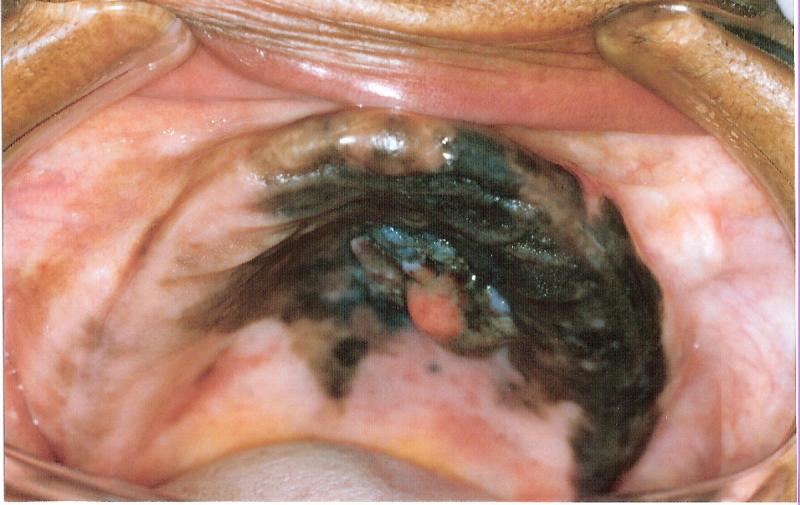
Primary mucosal melanoma arises from melanocytes in mucosal membranes rather than from a metastasis originating elsewhere. It is rare and includes different locations: nasal cavities and paranasal sinuses, oral cavity, anorectal region and genital mucosa, including the vulva and vagina. Oral disease may involve the palate and gums.
Reported proportions vary between populations and sites. The approximately 1% figure cited in some Western series is not universal; percentages with different denominators should not be added, and one sex ratio cannot describe the entire group. Conjunctival melanoma is generally considered separately and should not be confused with uveal melanoma.
Its relationship with sunlight differs from typical skin melanoma. Some sites are difficult to see, potentially delaying recognition, but location alone does not determine stage.
Appearance and site-related symptoms
A lesion may be an irregular brown or black patch, a nodule or an ulcerated mass. Poorly pigmented and amelanotic forms also occur. Absence of a dark mark therefore does not remove the need to investigate persistent symptoms.
Nasal sites may cause obstruction or bleeding; oral sites can produce a persistent lesion, bleeding or pain. Genital symptoms may include visible changes, itching, bleeding or pain during intercourse. Anorectal disease may cause bleeding, tenesmus or a mass, sometimes mistaken for a benign condition.
These manifestations are nonspecific. Persistent or changing symptoms need targeted assessment rather than photographic self-diagnosis or waiting for every possible sign.
Biopsy, staging and characterisation
Assessment involves the relevant site specialist alongside dermatology, oncology and pathology when needed. Dermoscopy may help on accessible surfaces but cannot replace examination and histology. Biopsy technique reflects size and anatomy, aiming for representative tissue without compromising subsequent management.
The team must establish whether the lesion is truly primary, assess local and distant extent and use staging appropriate to the site. Skin melanoma rules cannot all be transferred automatically to mucosal disease. Molecular testing may identify alterations relevant to targeted treatment; immunohistochemical positivity alone is not the same as an actionable mutation.
Treatment, function and prognosis
Surgery may be central when disease is resectable, balancing cancer control against functional consequences. More extensive surgery does not automatically guarantee better results. Radiotherapy may provide local control in selected settings.
Immunotherapy is an option in advanced disease. Targeted treatments require appropriate molecular alterations, such as certain KIT mutations. Responses and evidence are not identical to those for skin melanoma. Chemotherapy has selected uses, and clinical trials may be particularly relevant. The team checks indications, availability and patient circumstances.
Risk is often substantial, partly because diagnosis may occur at an advanced stage, but not every genital lesion or head-region melanoma has an invariably fatal outcome. Prognosis, follow-up and support depend on the individual case. Planning should address pain, nutrition, sexual or bowel function and quality of life where relevant.
Sources and update
- NCI — Melanoma Treatment (PDQ)
- EADO — European interdisciplinary melanoma guideline, treatment update 2024
Editorial revision: 17 October 2026. This information does not replace medical assessment. For very rare variants, some evidence comes from small series or case reports.