Origin and frequency
The choroid is the pigmented vascular layer beneath the retina. Choroidal melanoma originates in its melanocytes and belongs to the uveal melanomas, alongside iris and ciliary body forms. It is the most frequent uveal melanoma site and an important primary intraocular malignancy in adults.
It is rare in the general population and particularly in childhood. Adults and older people are affected more often, but a typical age is not an exclusion criterion. Many lesions appear without a previously recognised nevus; some melanomas develop in association with a choroidal nevus. Having a nevus does not mean inevitable transformation.
Incidence must be expressed as cases per population over a defined period, not as “1.5% per 100,000”. Estimates depend on the registry and may cover all uveal melanomas rather than the choroid alone. Historical annual Italian case figures should therefore not be treated as current counts.
Presentation and visual symptoms
Early lesions may be asymptomatic and found during fundus examination. Symptoms can include flashes, floaters, distorted images, missing areas of the visual field and reduced vision. Subretinal fluid or retinal detachment may contribute; involvement of the macula and fovea affects central vision.
Anterior lesions or extension towards the ciliary body may affect the lens and refraction, distort the pupil or cause secondary glaucoma. These findings are not exclusive to melanoma; examination and interpretation of the affected structures are needed.
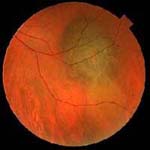
The lesion may be pigmented or amelanotic. Orange pigment related to lipofuscin and other findings help specialists assess activity and suspicion, but colour alone cannot establish diagnosis. Eye examination schedules should reflect age, symptoms and risk; this is not a universal cancer-screening prescription for everyone.
Diagnosis and similar lesions
Indirect ophthalmoscopy, clinical examination and A/B-scan ocular ultrasound are central to describing the lesion. Ultrasound measures thickness and configuration; photographs, OCT and other techniques document the retina and subretinal fluid. MRI, CT or angiography address specific questions rather than automatically being ordered together.
Differential diagnoses include choroidal nevus and haemangioma, retinal pigment epithelium hypertrophy, subretinal haemorrhage, choroidal metastasis, melanocytoma and osteoma. Comparison with earlier images can help but does not replace clinical judgement when a lesion is already suspicious.
Fine-needle or other biopsy may clarify diagnosis or provide prognostic information. It is not necessary in every case because many diagnoses rely on examination and imaging. The centre should explain the question the sample is intended to answer, sampling limitations and possible risks.
Dimensions and classification
Thickness and basal diameter are different measurements and should be reported with units and methods. “Small”, “medium” and “large” categories help discuss options, but thresholds depend on the classification used and are not an independent treatment formula.
Historical COMS criteria, often cited in treatment studies, classified medium tumours at approximately 2.5–10 millimetres in height with a basal diameter no greater than 16 millimetres; other definitions include additional conditions. These ranges should not be conflated with current TNM staging. Location, relationships with the optic disc and fovea, ciliary involvement and extension outside the eye complete the assessment.
Histology, chromosomes and prognosis
Traditional histology distinguishes spindle cells, epithelioid cells and mixed forms. Spindle cells have historically been described as types A and B, differing in nuclear shape and nucleolar prominence. Epithelioid cells are more polygonal, with conspicuous nuclei and nucleoli and abundant cytoplasm. These are pathology terms, not features identifiable by looking at the eye.
Generally, an epithelioid component is associated with greater risk than a spindle-cell component. Automatically attributing greater aggressiveness to spindle cells is incorrect. Mitotic activity, nucleoli, necrosis, inflammatory infiltrates and invasion of ocular structures are interpreted together rather than using one feature to determine prognosis.
Chromosome 3 monosomy and chromosome 8 abnormalities, especially 8q gain, are among findings associated with metastatic risk. FISH and other cytogenetic or molecular techniques may contribute to characterisation. Gene-expression profiling and alterations in genes such as BAP1 can provide further information in appropriate settings. A tumour finding does not automatically imply an inherited mutation; personal genetic investigation requires a specific indication.
Local treatment and visual function
For many medium-sized lesions, episcleral plaque brachytherapy or charged-particle radiotherapy treats the tumour while preserving the eye. Plaques may use radioisotopes such as iodine-125 or ruthenium-106 according to indication and availability. Proton therapy uses protons, not photons; helium beams have been used in separate historical or specialist settings.
COMS studies of medium tumours did not show a survival advantage for enucleation over iodine-125 brachytherapy. Selection also considers local control, complication risks and remaining vision. Eye removal should therefore not be presented as mandatory for every choroidal melanoma.
Very large or extensive tumours, or a painful and severely compromised eye, may require enucleation. Selected cases may be considered for specialist resection or other conservative strategies. Photocoagulation and transpupillary thermotherapy have limited or complementary roles and do not universally replace the main treatments.
Radiotherapy can lead to retinal damage, swelling, cataract or other complications requiring management. Anatomical eye preservation and vision preservation are not equivalent. Control of the mass, which may regress slowly, is assessed through measurements over time.
Systemic spread and current treatment
Uveal melanoma spreads mainly through the bloodstream and frequently involves the liver. Lung, bone and other organs may also be affected, including less common renal or ovarian sites; lymph node involvement is less typical than in skin melanoma. Surveillance is personalised and may include liver imaging. Normal liver blood tests alone cannot exclude metastasis.
Metastatic uveal disease should not automatically be equated with skin melanoma in prognosis or treatment response. Tebentafusp is authorised in the EU for HLA-A*02:01-positive adults with unresectable or metastatic uveal melanoma. Other patients or treatment settings may be considered for systemic options, liver-directed procedures and clinical trials at expert centres.
Chemotherapies such as fotemustine and vaccine approaches belong to a history of studies and selected uses; they are not standard answers equivalent to current options. Perfusion and other liver-directed treatments require specialist selection. A list of medicines cannot determine the appropriate choice.
Follow-up, prevention and useful questions
Historical mortality percentages after enucleation do not describe every patient and do not demonstrate that surgery causes spread. Prognosis and follow-up duration depend on individual risk; recurrence or metastasis can occur after a considerable interval.
UV-protective sunglasses support eye health, but the causal relationship between sunlight and choroidal melanoma is less established than for skin melanoma. Protective lenses alone cannot be promised to prevent this tumour. Ask the centre which dimensions and stage have been documented, what biological information is available and how the eye, vision and liver will be monitored.
Sources and update
Editorial revision: 17 October 2026. This information does not replace medical assessment. For very rare variants, some evidence comes from small series or case reports.