Blue nevus and associated melanoma
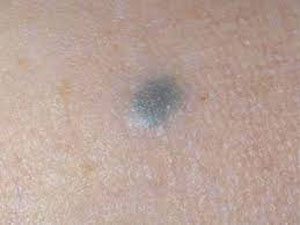
A blue nevus is generally a benign melanocytic lesion. Its blue or blue-grey colour reflects pigment deep in the dermis and the way light travels through tissue. Malignant transformation is rare; not every blue nevus should be regarded as early melanoma.
“Melanoma arising in a blue nevus” concerns a malignancy associated with this family of lesions. Literature also uses terms such as blue-nevus-like melanoma. Association with a pre-existing nevus needs documentation rather than inference from blue colour alone.
Historical descriptions include work by Allen and Spitz. The scalp and other sites, including extremities and trunk, appear in case series. A presumed peak age of 45 or male predominance does not provide universal diagnostic criteria.
Changes needing assessment
Persistent enlargement, a new nodule, ulceration, bleeding or change from the usual appearance needs assessment. Sizes described in individual tumour reports are not thresholds; a lesion need not reach several centimetres before being checked.
A new blue lesion in adulthood or a changing deep lesion may require differential diagnosis. Dermoscopy contributes, but the depth of some lesions limits its ability to describe the entire tissue. A photograph of a benign blue nevus explains the context and is not a proven example of melanoma.
The role of histology
The pathologist assesses the relationship between blue-nevus and suspicious components, atypia, mitotic activity, necrosis and architecture. Spindle or epithelioid cells may form bundles or nodules; giant cells and inflammatory infiltrates may occur. Not every feature is required, and the malignant component need not be confined to the edge.
Cellular blue nevi, atypical lesions and melanoma can be difficult to distinguish. Representative tissue is needed, with dermatopathology review for complex cases. Immunohistochemistry and selected molecular investigations support classification without replacing morphology.
Abundant pigment or an inflammatory infiltrate cannot alone establish benignity or malignancy. The complete report matters more than one word or an isolated image.
Treatment and surveillance
When melanoma is confirmed, assessment establishes extent, resectability and further investigation needs. It can behave aggressively, but small series cannot predict the same outcome for everyone. Depth and location require specialist interpretation of pathology findings.
Surgery is central to resectable disease; lymph node procedures and systemic treatment are discussed according to the whole situation. Blue colour does not identify a targeted treatment or replace molecular analysis when indicated.
A stable blue nevus may be managed differently from a changing lesion. Follow-up should match the actual diagnosis, avoiding both generalised alarm and reassurance based solely on a familiar mole-like appearance.
Sources and update
- NCI — Melanoma Treatment (PDQ)
- Cellular blue nevomelanocytic lesions — clinicopathological study
- Melanoma arising in association with blue nevus — study of 24 cases
Editorial revision: 17 October 2026. This information does not replace medical assessment. For very rare variants, some evidence comes from small series or case reports.